Author: Ken Dropiewski

XYRA Announces First Patient Dosed in Europe in the Phase 2/3 HARBOR-AF Study of Budiodarone in Paroxysmal and Persistent Atrial Fibrillation

LOS ALTOS, California, Aug. 31, 2026 (GLOBE NEWSWIRE) — Open-label, dose-escalation study using cardiac rhythm data from implantable and wearable AF monitors allows the treating physician to titrate the dose of budiodarone monthly. First European patient dosed in CLN-209 (HARBOR-AF)Study is the first to titrate an antiarrhythmic drug against continuously monitored AF burden (AFB) and long episodes of AF (LEAF) reported in real time from a range of wearable and implanted devicesHARBOR-AF study is starting as a 100 subject Phase 2 feasibility study in EU and will extend in 2027 to US sites as one of three Phase 3 pivotal registration studies the FDA requires for approval XYRA LLC, a private biopharmaceutical company committed to developing innovative therapies for cardiac rhythm disorders with high unmet need, today announced that the first patient in Poland has been dosed with budiodarone in HARBOR-AF (CLN-209), the company’s Phase 2/3 open-label, dose-escalation study evaluating budiodarone in subjects with paroxysmal and persistent atrial fibrillation (AF). HARBOR-AF is a global, multicenter, open-label, dose-escalation Phase 2/3 study of budiodarone in approximately 600 subjects with highly symptomatic paroxysmal and persistent AF who have failed rhythm control with antiarrhythmic drugs or AF catheter ablation, or who have failed rate control. The objective of the study is to determine, in a real-world setting, the effectiveness of dose-adjusted budiodarone therapy, guided by a range of currently available AF monitoring tools, in eliminating harmful LEAF greater than 5 hours over 6 months and reducing AF burden and symptoms. It will also help define the doses to be used in a future potential randomized, placebo-controlled registration study. HARBOR-AF is starting as a Phase 2 feasibility study in the European Union and is planned to extend to the United States as one of three Phase 3 pivotal registration studies the FDA requires for approval. Following a 28-day run-in period to confirm eligibility based on AF burden, multiple long episodes of AF (LEAF), and AF symptoms, subjects will enter a 6-month treatment period starting with budiodarone 200 mg twice daily. Treating physicians may escalate the dose monthly in 200 mg twice-daily increments, up to 800 mg twice daily, according to predefined responder criteria. Responder status is defined by the absence of LEAF greater than 5 hours and by maintaining cumulative AF burden below 5 hours or 21% in any rolling 24-hour period. The study is designed to identify, for each subject, the lowest effective dose of budiodarone that controls AF symptoms and suppresses prolonged AF episodes associated with increased risk of stroke, heart failure, and progression to permanent AF. This study uniquely integrates AF monitoring into both subject eligibility assessment and treatment response, using the resulting rhythm data to guide budiodarone dose titration. XYRA is using a range of implantable and wearable AF monitoring technologies available to cardiologists. Where present, AF data are collected from pre-implanted cardiac implantable electronic devices (CIEDs), including pacemakers and implantable loop recorders; when CIED data are not available, subjects are monitored using wearable devices. Rhythm data from either source are relayed to the treating physician and used to quantify AF burden and the number and duration of LEAF episodes monthly or quarterly. At each monthly visit, physicians review AF burden, LEAF, and Responder Status data to make individualized dose-titration decisions. Further details of the study design, eligibility criteria, and monitoring methods are available in the HARBOR-AF study listing on clinicaltrials.gov (NCT number: NCT07792239). “Evidence from large epidemiological studies indicates that stroke risk is influenced not only by the overall burden of atrial fibrillation but also by its pattern, particularly, prolonged episodes or clusters of episodes which we refer to as long episodes of AF, or LEAF. These are either discrete episodes of at least five hours or periods of daily AF burden exceeding five hours both readily identified in an individual with AF using modern digital technologies and AI tools, and probably long enough time in AF to form a clot in the left atrium.” said Peter Milner, M.D., FACC., founder and managing member of XYRA. “In the HARBOR-AF study, we plan to identify patients who experience frequent LEAF using a range of reliable, FDA-approved AF-monitoring technologies, including existing pacemakers and low-cost, convenient wearable devices such as patches and wristbands. Once each patient’s AF burden, risk profile, and symptoms have been established at baseline, we plan to administer budiodarone using a dose-escalation strategy to identify the appropriate dose for that individual over six months. Treatment will be guided by the AF-monitoring systems, with the aim of eliminating LEAF, thereby establishing a safe harbor, while reducing monthly AF burden and associated symptoms. We believe this study could establish a precedent of the first use of cardiac rhythm data collected from smart watches, beyond simply using them for irregular rhythm notifications.” Professor Andrzej Przybylski, M.D., Head of Cardiology, University of Rzeszów, Poland, and principal investigator at the first activated site, added, “We are pleased to be leading the clinical trial of budiodarone in Poland, the first antiarrhythmic drug to be individually dose adjusted to maximize its efficacy and safety using the wide range of AF monitoring tools currently available to us in practice. We believe that the combination of an investigational antiarrhythmic drug and AF monitoring tools may be a relatively low-cost solution to improve AF rhythm control and improve patient outcomes.” “The use of sophisticated continuous or near-continuous heart rhythm monitoring to assess AF-related stroke risk and guide individualized dose adjustment represents an exciting and innovative approach to evaluating the efficacy of budiodarone, a drug already well known to shorten or suppress episodes of atrial fibrillation,” said Professor A. John Camm, M.D., Emeritus Professor of Clinical Cardiology at City St George’s, University of London, a globally recognized leader in atrial fibrillation and long-standing advisor to the budiodarone program. “Joining XYRA as Chief Operating Officer at such a pivotal stage in the company’s development is immensely exciting. Having spent many years leading R&D and operations in large pharma, I joined XYRA because I strongly believe in the potential of budiodarone to transform outcomes for patients with AF,” said Charlie Rampersaud, XYRA’s Chief Operating Officer. “My immediate focus is on building the operational framework required to support next year’s randomized, placebo-controlled CLN-210 study.” Budiodarone is being developed under a regulatory pathway agreed with the FDA that incorporates wearable AF monitoring into the clinical development program and proposed labeling strategy. About Budiodarone Budiodarone is currently in Phase 2/3 clinical development and is a potentially first-in-class mixed ion channel blocker with esterase metabolism, with a significantly shorter half-life than amiodarone and no evidence of tissue accumulation in human or animal studies. In clinical studies to date, budiodarone has demonstrated reductions in AF burden and prolonged AF episodes, improvements in AF symptoms, and maintenance of sinus rhythm. About Atrial Fibrillation Atrial fibrillation (AF) is the most common sustained arrhythmia in adults, affecting more than 50 million people worldwide. It is associated with an increased risk of thromboembolism, impaired cardiac function, and other morbidities. While many patients experience symptomatic AF, the condition may also first be identified following a stroke, the development of left ventricular dysfunction, or incidentally. The management of AF has evolved as evidence supporting improved outcomes with rhythm-control strategies has accumulated. In appropriately selected patients, treatment increasingly aims to restore and maintain sinus rhythm rather than relying solely on ventricular rate control. Rhythm-control options include antiarrhythmic drugs (AADs), catheter ablation, or a combination of the two. About XYRA LLC XYRA LLC is a private biopharmaceutical company committed to developing innovative therapies for cardiac rhythm disorders with high unmet need. XYRA’s mission is to make AF management comparable to that of other common cardiac conditions like hypertension and hypercholesterolemia, in which upward dose titration of effective drugs, guided by simple, widely available monitoring tools to confirm compliance and response to therapy, has consistently improved outcomes. For information: www.xyra.us Media and Investor Relations Contact: press@xyra.us LinkedIn: Xyra, LLC

Acoramidis Demonstrates Reversal of Cardiac Structural Disease Progression and Functional Decline and Significantly Increases Days Alive and Free from Hospitalization in ATTR-CM

– Acoramidis is the first therapy shown to potentially reverse cardiac structural disease progression and functional decline through 42 months based on CMR imaging, with up to half of patients showing clinically meaningful improvement in cardiac function in the completer analysis – Patients treated with acoramidis were observed to have an unprecedented 65 additional days alive and out of the hospital by Month 36 versus baseline placebo patients – Acoramidis demonstrated long-term efficacy and safety through 54 months across variant ATTR-CM subgroups, including p.Val142Ile and non-p.Val142Ile. These findings were simultaneously published in the European Journal of Heart Failure PALO ALTO, Calif., Aug. 30, 2026 (GLOBE NEWSWIRE) — BridgeBio Pharma, Inc. (Nasdaq: BBIO) (“BridgeBio” or the “Company”), a commercial-stage, multi-product biopharmaceutical company focused on developing medicines for genetic conditions, presented new analyses from the Phase 3 ATTRibute-CM study of Attruby® (acoramidis) in transthyretin amyloid cardiomyopathy (ATTR-CM), including the cardiac magnetic resonance imaging (CMR) substudy and the open-label extension (OLE) at the European Society of Cardiology (ESC) Congress 2026. Acoramidis is the only selective small molecule, orally administered, near-complete (≥90%) transthyretin (TTR) stabilizer. “The clinical community is excited about the potential to restore heart health found in these data. For a long time, patients living with ATTR-CM could only hope for a stop to the otherwise relentless progression of disease. These new CMR data from ATTRibute-CM shows evidence of reversal in a meaningful proportion of individuals treated with acoramidis, with roughly half showing improved left ventricular systolic function in the completer analysis, more than 2x the proportion observed in the natural history from a NAC cohort or in ATTRibute-CM participants treated with placebo. These findings support acoramidis as a therapy capable of altering the trajectory of this otherwise progressive disease,” said Marianna Fontana, M.D. of University College London, UK. “For patients and clinicians navigating ATTR-CM, this is an exciting signal that the treatment paradigm is shifting toward a therapy that could actively restore heart health rather than only manage decline.” The CMR substudy of ATTRibute-CM and its open-label extension provide the first evidence from serial CMR that a therapy can potentially reverse disease progression through Month 42. The findings presented by Awais Sheikh, MBChB of the National Amyloidosis Centre, London, UK were evaluated using two complementary analytical approaches, which found: In a completer analysis, clinically meaningful improvement from baseline in left ventricular (LV) systolic function was observed in 54% of acoramidis-treated patients versus 20% of placebo-treated patients at Month 30, and in 53% of continuous-acoramidis patients at Month 42For context, only 26% of completers in an independent natural history cohort demonstrated improved LV systolic function by Month 24 – approximately half the rate observed with acoramidis, suggesting that this magnitude of improvement falls outside the expected natural course of diseaseIn a conservative analysis, long-term acoramidis treatment was associated with clinically meaningful improvement from baseline in LV systolic function in approximately one-third of patients over 30-42 months. Improvement was observed in 34% of acoramidis-treated patients versus 9% of placebo-treated patients at Month 30 and in 30% of continuous-acoramidis patients at Month 42In addition, 46% of patients receiving continuous acoramidis demonstrated improvement from baseline in LV mass index at Month 42, providing evidence of favorable structural remodelingThese results provided sufficient evidence for BridgeBio to recently dose its first participant in ASCEND-ATTR, a Phase 3b/4 study designed to determine if acoramidis is associated with sustained improvement in myocardial structural disease progression, function and amyloid burden In a post-hoc analysis of ATTRibute-CM presented by Richard Wright, M.D. of the Pacific Heart Institute, U.S., acoramidis preserved significantly more time alive outside the hospital for patients with ATTR-CM. The analysis evaluated days lost to death and/or cardiovascular-related hospitalization (DLDCVH), a patient-centered measure that integrates all-cause mortality, cardiovascular-related hospitalizations, and length of stay into a single assessment of disease burden. Key findings included: In participants with ATTR-CM, acoramidis reduced the estimated mean percentage of DLDCVH to 7.5% versus 11.7% with placebo through Month 30Acoramidis preserved more than one month of additional time alive and out of the hospital (38 days) over 30 months with the benefit nearly doubling to 65 days (observed) over three years, and nearly tripling to up to 94 days (modelled estimates) over three years, reflecting progressive divergence in outcomes over time The p.Val142Ile genetic variant is the most common ATTR-CM genetic variant globally, disproportionately affecting individuals of Western African ancestry, with a carrier frequency of 3-4% in the U.S. Black population. Findings in the ATTRibute-CM OLE presented by Kevin Alexander, M.D. of Stanford University School of Medicine, U.S. showed continued benefit of acoramidis in 56 variant ATTR-CM (ATTRv-CM) patients, including 35 p.Val142Ile and 21 non-p.Val142Ile patients through Month 54, demonstrating: All-cause mortality (ACM) and cardiovascular mortality (CVM) were markedly lower in the continuous acoramidis arm versus placebo-to-acoramidis across both p.Val142Ile and non-p.Val142Ile variant subgroupsThrough Month 54, ACM was 30.4% with continuous acoramidis versus 66.7% with placebo-to-acoramidis in the p.Val142Ile subgroup, and 24.3% with continuous acoramidis versus 57.9% with placebo-to-acoramidis across the overall ATTRv-CM population, a consistent, more than two-fold difference in mortality favoring continuous treatmentThe ACM and CVM rates at Month 54 were notably high (~65%) in the p.Val142Ile group who were randomized to placebo in ATTRibute-CM, underscoring the substantial unmet medical need in this high-risk subgroupContinuous acoramidis achieved sustained increases in serum TTR (sTTR) and persistent attenuation of N-terminal pro-B-type natriuretic peptide (NT-proBNP) rise through Month 54 in both participants with p.Val142Ile or non-p.Val142Ile variantsThese Month 54 findings extend the survival benefit and favorable biomarker trends previously reported at Month 30, demonstrating the long-term durability of efficacy and safety of acoramidis in ATTRv-CM, including in the p.Val142Ile subgroupAcoramidis remained well tolerated through Month 54, with no new safety signals observed in the OLE In addition to the one oral presentation and two moderated posters highlighted, two additional moderated posters on acoramidis were shared at the ESC Congress 2026, including: Acoramidis Improves Health-Related Quality of Life in Wild-Type and Variant Transthyretin Amyloid Cardiomyopathy: An EQ-5D-5L Subgroup Analysis from ATTRibute-CM, presented by Emer Joyce, M.D., Ph.D. of The Mater Misericordiae University Hospital, IE Treatment with acoramidis resulted in significant and clinically meaningful benefits in health-related quality of life (HRQoL) in both wild-type ATTR-CM (ATTRwt-CM) and ATTRv-CM. Greater impact on HRQoL versus placebo was observed in participants with ATTRv-CM Improvement of Health Status with Acoramidis in Patients with Wild-Type and Variant Transthyretin Amyloid Cardiomyopathy: KCCQ Domains Analysis from the ATTRibute-CM Study, presented by Nitasha Sarswat, M.D. of University of Chicago Medical Center, U.S. In ATTRibute-CM, acoramidis attenuated the decline in heart failure-related health status versus placebo in participants with ATTRwt-CM and ATTRv-CM, with consistent benefits observed across Kansas City Cardiomyopathy Questionnaire Overall Summary (KCCQ-OS) and individual domain scores. A numerical improvement was observed across almost all KCCQ domains in acoramidis-treated participants with ATTRwt-CM and ATTRv-CM relative to placebo As part of BridgeBio’s partnership with Yale’s Cardiovascular Data Science (CarDS) Lab to advance AI networks for earlier detection of ATTR-CM, three posters were presented at the ESC Congress 2026. Findings from the partnership included: A Novel AI-Derived Digital Biomarker for Monitoring Disease Progression in ATTR-CM: First-In-Trial Use of a Computer Vision AI-ECG Algorithm within a Phase 3 Pivotal Randomized Controlled Trial, presented by Rohan Khera, M.D. of Yale School of Medicine, U.S. This showed the first deployment of a computer vision AI-ECG algorithm, operating directly on ECG data, as a digital biomarker in a RCT (ATTRibute-CM). An image-based AI-ECG algorithm demonstrated discrimination across clinical subgroups at baseline and detected differential longitudinal changes between acoramidis and placebo over 30 months. These findings support the potential role of AI-ECG derived prediction scores as a scalable digital biomarker in clinical trials and potential routine cardiovascular care A Fully Decentralized, Patient-Led Digital Registry for ATTR-CM Integrating Multisystem EHR and Wearable Data: The DISCOVER-ATTR Study, presented by Aline Pedroso, Ph.D. of Yale School of Medicine A fully decentralized, patient-led digital registry can successfully aggregate longitudinal multisystem electronic health records (EHR) data and wearable physiologic signals in ATTR-CM. Early results show substantial data yield and feasibility of longitudinal mapping of care trajectories and multimodal risk prediction, providing a blueprint for next-generation registries in rare cardiovascular diseases Nationwide U.S. Federated Deployment of Artificial Intelligence for Multimodal Screening of ATTR Cardiomyopathy: First Multicenter Analysis from the TRACE-AI Network, presented by Bruno Batinica, MBChB of Yale School of Medicine In this largest-ever deployment of AI-electrocardiogram and AI-Echo models for opportunistic retrospective screening of individuals at risk of ATTR-CM, we demonstrate a large burden of probable undiagnosed ATTR-CM with prognostic implications. Leveraging this framework for screening holds promise for enabling broad, timely identification of patients to maximize the overall benefit of new therapies Acoramidis is approved as Attruby® by the U.S. FDA and is approved as BEYONTTRA® by the European Medicines Agency (EMA), Japanese Pharmaceuticals and Medical Devices Agency, Swissmedic, the Swiss Agency for Therapeutic Products, the UK Medicines and Healthcare Products Regulatory Agency, and the Brazilian Health Regulatory Agency (ANVISA) with all labels specifying near-complete stabilization of TTR. Additional data on the benefit of Attruby for individuals with ATTR-CM is planned for future medical meetings, including Heart Failure Society of America (HFSA) Annual Scientific Meeting 2026, taking place in Phoenix, Arizona on October 9-12, 2026. About Attruby® (acoramidis)INDICATIONAttruby is a transthyretin stabilizer indicated for the treatment of the cardiomyopathy of wild-type or variant transthyretin-mediated amyloidosis (ATTR-CM) in adults to reduce cardiovascular death and cardiovascular-related hospitalization. IMPORTANT SAFETY INFORMATIONAdverse ReactionsDiarrhea (11.6% vs 7.6%) and upper abdominal pain (5.5% vs 1.4%) were reported in patients treated with Attruby versus placebo, respectively. The majority of these adverse reactions were mild and resolved without drug discontinuation. Discontinuation rates due to adverse events were similar between patients treated with Attruby versus placebo (9.3% and 8.5%, respectively). BridgeBio Forward-Looking StatementsThis press release contains forward-looking statements. Statements in this press release may include statements that are not historical facts and are considered forward-looking within the meaning of Section 27A of the Securities Act of 1933, as amended (the Securities Act), and Section 21E of the Securities Exchange Act of 1934, as amended (the Exchange Act), which are usually identified by the use of words such as “anticipates,” “believes,” “continues,” “estimates,” “expects,” “hopes,” “intends,” “may,” “plans,” “projects,” “remains,” “seeks,” “should,” “will,” and variations of such words or similar expressions. BridgeBio intends these forward-looking statements to be covered by the safe harbor provisions for forward-looking statements contained in Section 27A of the Securities Act and Section 21E of the Exchange Act. These forward-looking statements include statements regarding the potential clinical significance and therapeutic implications of the data presented regarding acoramidis, including the potential clinical and therapeutic implications of observed changes in cardiac structure and function and the potential for acoramidis to alter the trajectory of ATTR-CM and restore heart health; the potential utility of AI-based tools and digital biomarkers for the detection, monitoring and screening of ATTR-CM in clinical trials and clinical practice; and BridgeBio’s plans to present additional data regarding Attruby at future medical meetings. Although the Company believes that its plans, intentions, expectations and strategies as reflected in or suggested by those forward-looking statements are reasonable, the Company can give no assurance that the plans, intentions, expectations or strategies will be attained or achieved. Furthermore, actual results may differ materially from those described in the forward-looking statements and will be affected by a number of risks, uncertainties and assumptions, including, but not limited to, initial and ongoing data from the Company’s clinical trials not being indicative of final data, the design and success of ongoing and planned clinical trials, the risk that results from post hoc analyses, subgroup analyses or other analyses may not be predictive of future clinical outcomes or treatment effects, that observed improvements in cardiac structure, function or other measures may not be replicated in additional analyses or studies or translate into improved long-term clinical outcomes, that the potential utility of AI-based tools and digital biomarkers may not be demonstrated in further studies or translate into routine clinical use, that plans to present additional data may change, the impacts of current macroeconomic and geopolitical events, including changing conditions from hostilities in Ukraine and in Israel and the Middle East, increasing rates of inflation and changing interest rates, on business operations and expectations, as well as those risks set forth in the Risk Factors section of the Company’s most recent Quarterly Report on Form 10-Q and Annual Report on Form 10-K and the Company’s other filings with the U.S. Securities and Exchange Commission. Moreover, the Company operates in a very competitive and rapidly changing environment in which new risks emerge from time to time. These forward-looking statements are based upon the current expectations and beliefs of the Company’s management as of the date of this press release, and are subject to certain risks and uncertainties that could cause actual results to differ materially from those described in the forward-looking statements. Except as required by applicable law, BridgeBio assumes no obligation to update publicly any forward-looking statements, whether as a result of new information, future events or otherwise. About BridgeBioBridgeBio exists to develop transformative medicines for genetic conditions. Millions of people worldwide living with genetic conditions lack treatment options, often because drug development for small patient populations can be commercially challenging. We aim to bridge the gap between advancements in genetic science and meaningful medicines for underserved patient populations. Our decentralized, hub-and-spoke model is designed for speed, precision, and scalability. Autonomous and empowered teams focus on individual conditions, while a central hub provides the clinical, regulatory, and commercial capabilities needed to bring innovation to market. For more information, visit bridgebio.com and follow us on LinkedIn, X, Facebook, Instagram, YouTube, and TikTok. BridgeBio Media Contact:Kaitlyn Reilly, Director, Communicationscontact@bridgebio.com(650) 789-8220 BridgeBio Investor Contact:Kristen Kelleher, Director, Investor Relationsir@bridgebio.com

Bayer Announces Phase III REVEAL Study with Investigational PET Radiotracer Iodine 124 Evuzamitide Presented as Late-Breaker at ESC 2026

WHIPPANY, N.J.–(BUSINESS WIRE)–Bayer today announced the presentation of first detailed results from the Phase III REVEAL study, an investigator-initiated study by Brigham and Women’s Hospital, that evaluated the investigational positron emission tomography (PET) radiotracer iodine 124 evuzamitide (I 124 evuzamitide) for the diagnosis of cardiac amyloidosis.1 The pivotal study met its primary endpoints in the assessment of sensitivity and specificity for the diagnosis of cardiac amyloidosis b

CRISPR Therapeutics Presents Phase 1a Data for CTX310® Demonstrating Deep and Durable ANGPTL3 Editing, Triglyceride and LDL Lowering at ESC Congress 2026

-Data presented in a late-breaking presentation at the European Society of Cardiology (ESC) Congress 2026- -Phase 1a clinical data for CTX310® continued to demonstrate robust, dose-dependent reductions in circulating ANGPTL3 with a mean reduction from baseline of 79% (maximum 89%), a mean reduction in triglycerides (TG) of 48% (maximum 78%), and a mean reduction of low-density lipoprotein (LDL) of 53% (maximum 84%) at the highest dose- -CTX310 was well tolerated with no treatment-related serious adverse events, no ≥Grade 3 changes in liver transaminases, and no additional treatment-related adverse events since the previous update- -Findings simultaneously published in The New England Journal of Medicine entitled “Durability of CRISPR-Cas9 Gene Editing Targeting ANGPTL3 with CTX310”- ZUG, Switzerland and BOSTON, Aug. 28, 2026 (GLOBE NEWSWIRE) — CRISPR Therapeutics (Nasdaq: CRSP) today presented durability data from its Phase 1a clinical trial evaluating CTX310®, an investigational, in vivo CRISPR/Cas9 gene editing therapy targeting ANGPTL3. A single-course treatment with CTX310 produced deep and durable reductions in circulating ANGPTL3, triglycerides (TG), and low-density lipoprotein (LDL) that were sustained through one year of follow-up. At the highest dose, mean reductions from baseline were 79% (maximum 89%) for ANGPTL3, 48% (maximum 78%) for TG, and 53% (maximum 84%) for LDL. These extended follow-up data demonstrate the durability of CTX310’s effect and support its potential to deliver long-lasting lipid lowering after a single intravenous (IV) infusion. These data were presented today during a late breaking session at the European Society of Cardiology (ESC) Congress 2026 and extend the Phase 1 results previously presented. The data were also published today in The New England Journal of Medicine (NEJM) in a peer reviewed article entitled “Durability of CRISPR-Cas9 Gene Editing Targeting ANGPTL3 with CTX310.” CRISPR Therapeutics is advancing CTX310 in a Phase 1b clinical trial, with U.S. and ex-U.S. trials ongoing, and expects to provide an additional update on the CTX310 program in the second half of 2026. “These durability data mark an important next step for the CTX310 program and for the field of in vivo gene editing,” said Naimish Patel, M.D., Chief Medical Officer, CRISPR Therapeutics. “Evidence that a single dose can produce lasting lipid lowering is central to our goal of developing one-time treatments for cardiometabolic diseases. These results provide strong support for continued advancement of CTX310 and our broader cardiovascular gene editing portfolio, and we look forward to sharing new data from the severe hypertriglyceridemia cohort of the CTX310 Phase 1b trial in the second half of this year.” “For patients at high cardiovascular risk, the biggest challenge is often not starting therapy but staying on it, since daily medications require lifelong adherence that many patients are unable to maintain,” said Luke Laffin, M.D., principal investigator and Medical Director of the Cleveland Clinic Coordinating Center for Clinical Research. “A single infusion producing durable reductions at one-year is an encouraging signal that a one-time approach could help close that adherence gap.” “What is compelling about this update is that the reductions in ANGPTL3, triglycerides, and LDL from a single infusion have persisted out to one-year, suggesting a sustained biological effect,” said Steven E. Nissen, M.D., senior author of the study and Chief Academic Officer at the Cleveland Clinic Heart, Vascular and Thoracic Institute. “A one-time treatment with this degree of durability could represent a meaningful advance in how we manage lifelong lipid disorders.” Phase 1a Clinical Trial Design The Phase 1a portion of the study was an open label, dose-escalation trial evaluating single-course IV doses of CTX310 ranging from 0.1 to 0.8 mg/kg (lean body weight) targeting ANGPTL3 in four patient groups: homozygous familial hypercholesterolemia (HoFH), severe hypertriglyceridemia (sHTG), heterozygous familial hypercholesterolemia (HeFH), or mixed dyslipidemias (elevated TG and LDL). Eligible participants had uncontrolled TG levels >150 mg/dL and/or LDL cholesterol >100 mg/dL (or >70 mg/dL for those with established ASCVD) despite background standard of care per local guidelines. The majority of participants were receiving statins and/or ezetimibe, while 40% were taking PCSK9 inhibitors. The trial was designed to evaluate safety and tolerability as primary endpoints, with changes in circulating ANGPTL3 protein, TG, and LDL as secondary endpoints.   Safety and Tolerability Single-course ascending doses of CTX310 were administered to 15 participants across sequential cohorts, and all participants completed at least one-year of follow-up as of the data cutoff. CTX310 was generally well tolerated, and no dose-limiting toxicities or serious adverse events related to treatment. Adverse events were generally mild to moderate. As previously reported in Laffin et al. (2025), one participant experienced an allergic reaction that resolved the following day with supportive care. Infusion-related reactions occurred in three participants (two at 0.6 mg/kg and one at 0.8 mg/kg dose), all Grade 2. All events resolved, and all participants completed their infusions. Beyond the transient aminotransferases elevation previously reported in one participant shortly after treatment, there were no liver function test elevations throughout the remainder of the trial. The safety events described above were previously reported in Laffin et al. (New England Journal of Medicine, 2025) and reflect the initial treatment period of the Phase 1a clinical trial. No new treatment-related safety events were observed during extended follow-up. Efficacy Highlights These new results build upon previously disclosed clinical data from 15 participants across four sequential cohorts, corresponding to lean body weight-based doses of DL1 [0.1 mg/kg], DL2 [0.3 mg/kg], DL3 [0.6 mg/kg], DL3.5 [0.7 mg/kg] and DL4 [0.8 mg/kg]. All participants had at least one-year of follow-up. Dose dependent reductions in circulating ANGPTL3 protein were sustained through one-year following CTX310 infusion.Among participants treated at 0.8 mg/kg, ANGPTL3 reductions of up to 89% were observed, with a mean reduction of 79% at one-year following CTX310 infusion. Next Steps The Phase 1b portion of the trial examines a fixed flat dose regimen of CTX310 equivalent to the most efficacious dose in Phase 1a (0.8mg/kg). CRISPR Therapeutics continues to anticipate sharing an update from the CTX310 Phase 1b clinical trial in the second half of 2026, focused on severe hypertriglyceridemia patients. About In Vivo Liver Editing Programs CRISPR Therapeutics has established a proprietary lipid nanoparticle (LNP) delivery platform to enable gene editing in the liver using both CRISPR/Cas9 and its novel, proprietary SyNTase™ editing technology. The Company’s in vivo portfolio includes three cardiovascular programs: CTX310, targeting angiopoietin-related protein 3 (ANGPTL3), in development for heterozygous and homozygous familial hypercholesterolemia, mixed dyslipidemias, and severe hypertriglyceridemia; CTX340™, targeting angiotensinogen (AGT), in development for refractory hypertension; and CTX321™, targeting LPA, in development for patients with elevated lipoprotein(a) [Lp(a)]. In addition, the Company’s disclosed development candidates also include CTX460™, targeting SERPINA1 using SyNTase editing, for the treatment of alpha-1 antitrypsin deficiency (AATD). About CRISPR Therapeutics CRISPR Therapeutics is a leading biopharmaceutical company focused on developing transformative gene-based medicines for serious human diseases. Founded over a decade ago as an early pioneer in CRISPR/Cas9 gene editing, the Company has evolved from a pioneering research-stage organization into an industry leader, marking a historic milestone with the approval of CASGEVY® (exagamglogene autotemcel [exa-cel]), the world’s first CRISPR-based therapy, for eligible patients with sickle cell disease and transfusion-dependent beta thalassemia. Today, CRISPR Therapeutics is advancing a broad, diversified pipeline spanning hemoglobinopathies, cardiovascular disease, autoimmune disease, oncology, regenerative medicine and rare diseases. The Company is also expanding its gene editing toolkit through SyNTase™ editing, its novel, proprietary platform designed to enable precise, efficient, and scalable gene correction. To accelerate its impact, CRISPR Therapeutics has established strategic collaborations with leading biopharmaceutical partners, including Vertex Pharmaceuticals. CRISPR Therapeutics AG is headquartered in Zug, Switzerland, with its wholly-owned U.S. subsidiary, CRISPR Therapeutics, Inc., and R&D operations based in Boston, Massachusetts and San Francisco, California. To learn more, visit www.crisprtx.com. CRISPR THERAPEUTICS® standard character mark and design logo, CTX310®, CTX321™, CTX340™, CTX460™ and SyNTase™ are trademarks and registered trademarks of CRISPR Therapeutics AG. All other trademarks and registered trademarks are the property of their respective owners. Reference Laffin L, et al. Phase 1 Trial of CRISPR-Cas9 Gene Editing Targeting ANGPTL3. The New England Journal of Medicine. 2025. CRISPR Special Note Regarding Forward-Looking Statements Statements contained in this press release regarding matters that are not historical facts are “forward-looking statements” within the meaning of the Private Securities Litigation Reform Act of 1995. Because such statements are subject to risks and uncertainties, actual results may differ materially from those expressed or implied by such forward-looking statements. Such statements include, but are not limited to, statements regarding any or all of the following: (i) CRISPR Therapeutics preclinical studies, clinical trials and pipeline products and programs, including, without limitation, manufacturing capabilities, status of such studies and trials, potential expansion into new indications and expectations regarding data, safety and efficacy generally; (ii) data included in the above-described oral presentation and any associated abstracts or posters, data included in the above-described article in The New England Journal of Medicine, as well as the ability to use data from ongoing and planned clinical trials for the design and initiation of further clinical trials; and (iii) the therapeutic value, development, and commercial potential of gene editing technologies and therapies, including CRISPR/Cas9 and SyNTase, as well as other technologies. Risks that contribute to the uncertain nature of the forward-looking statements include, without limitation, the risks and uncertainties discussed under the heading “Risk Factors” in CRISPR Therapeutics most recent annual report on Form 10-K and in any other subsequent filings made by CRISPR Therapeutics with the U.S. Securities and Exchange Commission. Existing and prospective investors are cautioned not to place undue reliance on these forward-looking statements, which speak only as of the date they are made. We disclaim any obligation or undertaking to update or revise any forward-looking statements contained in this press release, other than to the extent required by law. Investor Contact: +1-617-307-7503 ir@crisprtx.com Media Contact: +1-617-315-4493 media@crisprtx.com

Cytokinetics Announces Positive Results from ACACIA-HCM Presented in Hot Line Session at the European Society of Cardiology (ESC) Congress 2026 and Published in The New England Journal of Medicine

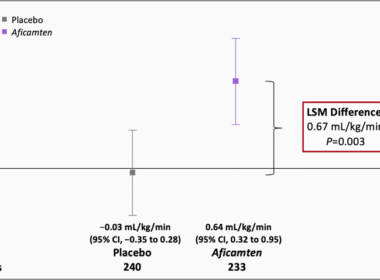
ACACIA-HCM is the First Phase 3 Clinical Trial to Successfully Demonstrate Statistically Significant Improvements Across Both Patient-Reported and Physician-Assessed Endpoints in Non-Obstructive HCM Supplemental New Drug Application to be Submitted to FDA in Fourth Quarter Company to Host Investor Event and Webcast Today at 2:00 PM Central European Summer Time (8:00 AM Eastern Time) SOUTH SAN FRANCISCO, Calif., Aug. 28, 2026 (GLOBE NEWSWIRE) — Cytokinetics, Incorporated (Nasdaq: CYTK) today announced the primary results from ACACIA-HCM (Assessment Comparing Aficamten to Placebo on Cardiac Endpoints In Adults with Non-Obstructive HCM), the pivotal Phase 3 clinical trial of aficamten in patients with symptomatic non-obstructive hypertrophic cardiomyopathy (nHCM) were presented in a Hot Line Session at the European Society of Cardiology (ESC) Congress 2026 in Munich, Germany, and simultaneously published in The New England Journal of Medicine.1 ACACIA-HCM met both dual primary endpoints, demonstrating statistically significant improvements from baseline to Week 36 compared to placebo in both Kansas City Cardiomyopathy Questionnaire Clinical Summary Score (KCCQ-CSS) and maximal exercise performance (pVO2). Results for the dual primary endpoint analysis consistently favored aficamten across prespecified subgroups studied. Based on the positive results from ACACIA-HCM, Cytokinetics plans to submit a supplemental New Drug Application to the U.S. Food and Drug Administration (FDA) for aficamten for the treatment of adult patients with symptomatic nHCM in the fourth quarter of 2026. “ACACIA-HCM is the first-ever positive clinical trial in non-obstructive HCM,” said Stephen Heitner, M.D., Cytokinetics’ Chief Medical Officer. “As shown in presentation and publication, the results from ACACIA-HCM are both statistically robust, consistent across prespecified subgroups and other secondary endpoints, and clinically impactful for these patients with non-obstructive HCM. As such, these data may potentially translate into a new treatment option for patients with HCM with no available medical treatments that directly address their underlying disease. If approved, we look forward to seeing aficamten become the first cardiac myosin inhibitor to treat the full spectrum of symptomatic HCM.” “We are grateful to the patient community and the clinical trial team who contributed to the successful completion of ACACIA-HCM, a fitting tribute to the patients and families who have struggled with this disease for many years and across generations. We are also pleased that most of the eligible patients from ACACIA-HCM are continuing treatment with aficamten in FOREST-HCM,” said Ahmad Masri, M.D., M.S., Director, Hypertrophic Cardiomyopathy Center and Cardiac Amyloidosis Program, Oregon Health & Science University and Principal Investigator of ACACIA-HCM. “We look forward to applying this study’s groundbreaking scientific knowledge into clinical practice upon potential approval, addressing this area of HCM where patients do not have adequate treatment options.” ACACIA-HCM: Efficacy The baseline characteristics of patients enrolled in ACACIA-HCM were well-matched between treatment groups and consistent with a symptomatic nHCM phenotype with substantial disease burden despite normal left ventricular ejection fraction (LVEF). There were two pre-specified primary endpoints, KCCQ-CSS and pVO₂, evaluated in parallel. For each endpoint, a p-value of 0.025 or less was considered statistically significant. Compared to placebo, treatment with aficamten demonstrated statistically significant improvements in both dual primary endpoints at 36 weeks (Table 1). Table 1: Dual Primary Endpoint Results PrimaryEndpointsChange from Baseline to Week 36LSM [95% CI]Aficamtenvs PlaceboLSM (95% CI)P-value AficamtenPlacebo  KCCQ-CSS11.4 [9.6 – 13.2]8.4 [6.6 – 10.2]3.0 (0.5 – 5.5)0.021pVO2 (ml/kg/min)0.64 [0.32 – 0.95]-0.03 [-0.35 – 0.28]0.67 (0.22 – 1.1)0.003LSM = least square mean; CI = confidence interval Improvements in KCCQ-CSS relative to placebo were noted beyond titration and throughout the treatment period in participants treated with aficamten, such that patients remaining on treatment at 72 weeks demonstrated a least square mean (LSM) change from baseline in KCCQ-CSS of 7.0 points. Of note, following a washout of aficamten for four weeks, the KCCQ-CSS declined from the end of treatment for participants on aficamten to match that in the placebo group (Figure 1). Figure 1: Assessment of KCCQ-CSS The figure is based on the observed data, except that the inset box of Week 36 LSM difference and p-value are from the primary analysis imputed data. At Week 36, pVO2 increased for participants on aficamten while it remained unchanged for participants on placebo (Figure 2). Figure 2: Assessment of pVO2 The treatment effect of aficamten on both dual primary endpoints was consistent across all prespecified subgroups, including baseline LVEF, atrial fibrillation status, genotype, age, sex, whether patients were receiving background beta-blocker therapy and whether patients had intracavitary obstruction at baseline (Figure 3). Figure 3: Pre-Specified Subgroups for KCCQ-CSS and pVO2 Statistically significant improvements compared to placebo were observed in key ranked secondary endpoints, including New York Heart Association (NYHA) Functional Class, the composite z-score of two cardiopulmonary exercise testing (CPET) parameters (VE/VCO2 and pVO2), and NT-proBNP, a biomarker of cardiac wall stress. Statistical significance was not met on the endpoints of change from baseline in left atrial volume index or the time to first cardiovascular event for aficamten compared to placebo (Table 2). Table 2: Secondary Endpoints SecondaryEndpointsChange from Baseline to Week 36LSM (95% CI)Aficamten vsPlaceboTreatmentDifference (95% CI)P-value AficamtenPlacebo  Improvement of ≥1 NYHA class at week 36 – n (%)108 (41.9)72 (27.8)14.1 (6.0 to 22.2)

New Daiichi Sankyo Data Underscore the Effect of Bempedoic Acid in the Real-World Management of Dyslipidemia and Cardiovascular risk

MUNICH–(BUSINESS WIRE)–Daiichi Sankyo (TSE:4568) today announced new results from the MILOS study that demonstrate the real-world impact of bempedoic acid administered either alone or as a fixed-dose combination with ezetimibe, in the management of dyslipidaemia. Presented at the European Society of Cardiology Congress 2026 in Munich, the findings show that the clinically relevant reductions in low-density lipoprotein cholesterol (LDL-C) achieved within the first year of treatment are estimat